
By Dr. John A. Robinson, NMD, and Dr. Cristina Romero-Bosch, NMD | Co-Founders, RegeneZone™
What if the source of your joint pain isn't just the cartilage that's wearing away, but the living bone beneath it?
For decades, we've been told that osteoarthritis is primarily a disease of cartilage degeneration. Cartilage wears down, joints become painful, and eventually patients are told they need a joint replacement.
We've never believed that explanation tells the whole story.
After nearly two decades of caring for patients with chronic musculoskeletal conditions, we've come to appreciate something increasingly supported by research: a joint is not simply a collection of mechanical parts. It is a living, biologically active system influenced by inflammation, metabolism, hormones, circulation, and muscle function.
One important development in osteoarthritis research involves something many patients have never heard of: bone marrow lesions (BMLs).
Understanding these lesions helps explain why we developed the RegeneZone Method™ around comprehensive joint evaluation and treatment rather than simply focusing on an injection.
What Is a Bone Marrow Lesion?
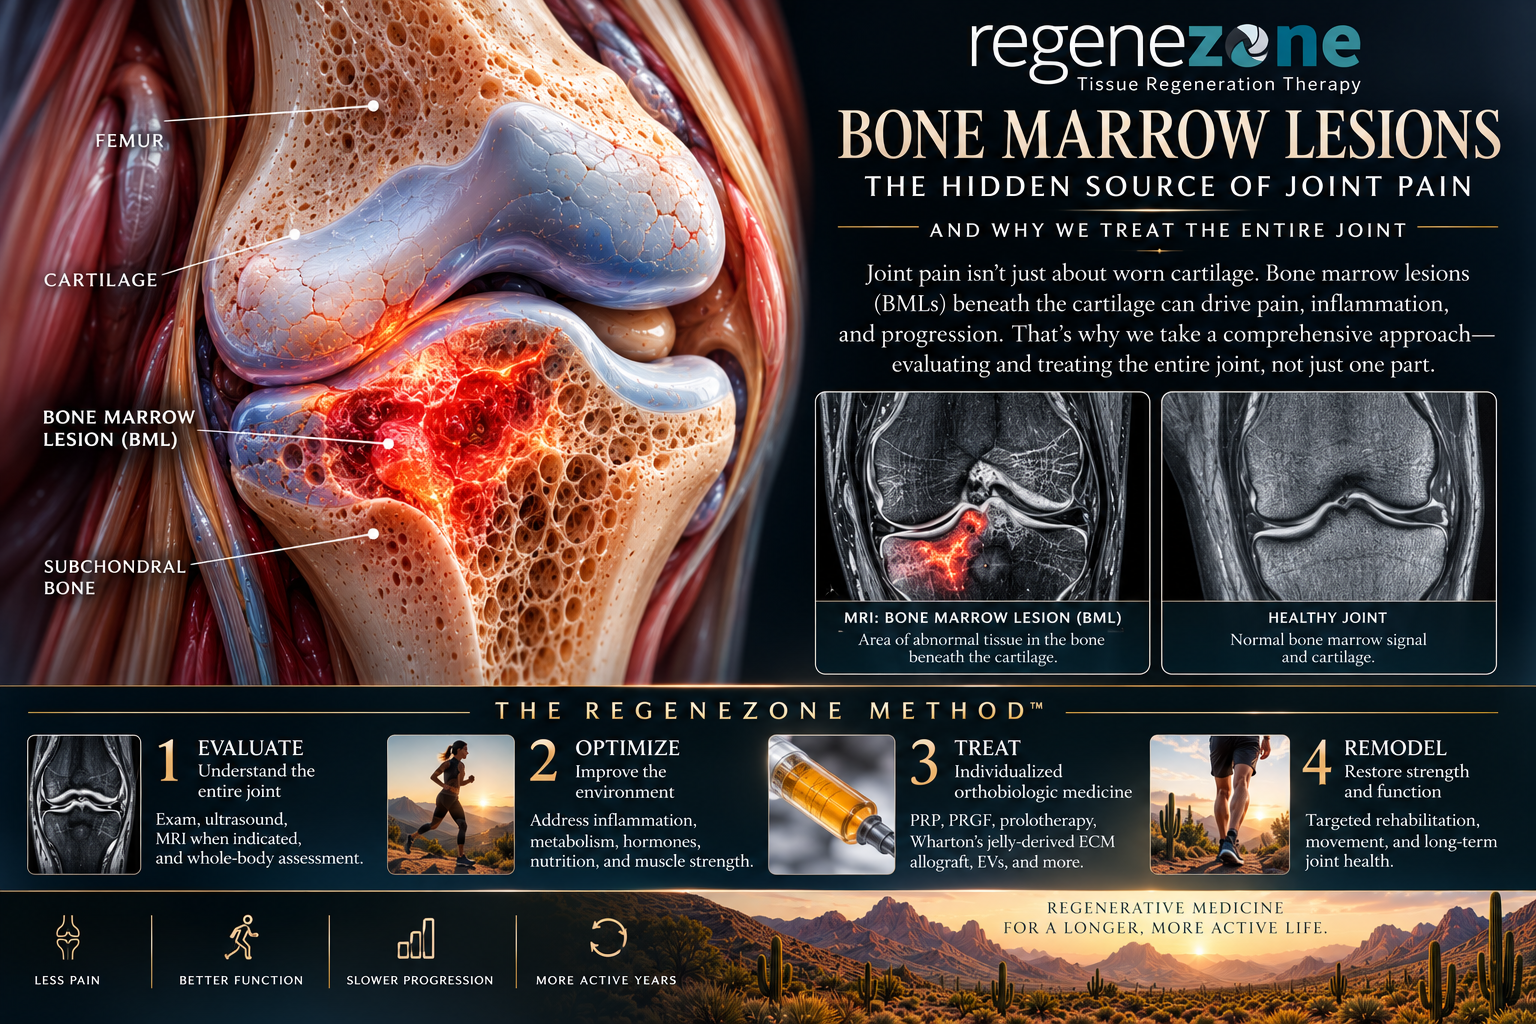
Beneath the cartilage covering the ends of our bones lies the subchondral bone. This structure supports cartilage, distributes mechanical forces, and participates in the joint's ongoing biological activity.
Within this bone, MRI sometimes reveals abnormalities known as bone marrow lesions.
Although often described as bone marrow edema, BMLs involve more than fluid accumulation. They may include microscopic bone damage, abnormal remodeling, inflammatory activity, fibrosis, and changes in circulation.
Why does this matter?
Because the bone beneath cartilage contains nerves and blood vessels, unlike the cartilage itself. Subchondral bone abnormalities may therefore contribute significantly to osteoarthritis pain.
The cartilage may be damaged, but the bone beneath it may be an important reason the joint hurts.
What the Research Tells Us
One particularly interesting investigation comes from the Multicenter Osteoarthritis Study (MOST), which followed patients using MRI over 30 months.
Researchers examined 395 knees and found that bone marrow lesions were not necessarily permanent. Approximately half of the existing lesions decreased in size or resolved during follow-up.
More importantly, changes in these lesions were associated with cartilage deterioration.
Compared with regions containing stable BMLs, areas where lesions enlarged had approximately 2.8 times the odds of subsequent cartilage loss. Areas developing new lesions had approximately 3.5 times the odds.
These findings demonstrate an important association between subchondral bone abnormalities and cartilage degeneration, although they do not establish direct causation.
For us, the message is clear: if we're evaluating a degenerating joint, we need to understand what's happening beneath the cartilage.
The Joint Is Constantly Communicating
Perhaps the most fascinating aspect of this research is what scientists call bone–cartilage crosstalk.
Cartilage, bone, synovial tissue, and surrounding structures communicate through inflammatory mediators, growth factors, immune signaling, and mechanical forces.
Researchers have identified pathways involving inflammatory cytokines such as IL-1β, IL-6, and TNF-α, along with matrix-degrading enzymes, bone-remodeling signals, and vascular changes.
These pathways can influence cartilage deterioration and subchondral bone remodeling.
This challenges the traditional idea that joint degeneration is simply inevitable mechanical wear and tear.
The joint is biologically active, constantly responding to its environment—and that environment is influenced by far more than age.
Why We Look Beyond the Joint
When patients come to RegeneZone with knee pain, we're not interested only in identifying where to place a needle.
We want to understand why that joint is deteriorating and which contributing factors we can address.
Is there chronic inflammation? Insulin resistance? Excess body fat? Loss of muscle strength? Hormonal deficiency? Poor bone health? Abnormal biomechanics?
These questions matter because osteoarthritis develops within a much larger physiological environment.
We pay particular attention to hormonal health. In women, declining estrogen during menopause influences bone remodeling, muscle physiology, and body composition. In men, clinically significant testosterone deficiency can contribute to declining muscle mass, reduced bone density, and diminished performance.
Hormone replacement is not an established treatment for reversing osteoarthritis or bone marrow lesions. However, addressing relevant deficiencies can be an important part of overall musculoskeletal care.
Our integration with The Hormone Zone® allows us to evaluate both the joint and the systemic factors influencing a patient's health.
Can We Treat the Bone Marrow Environment?
This is an emerging area of orthopedic and regenerative medicine research.
Investigators have explored intraosseous injections of platelet-rich plasma (PRP) and plasma rich in growth factors (PRGF), sometimes combined with conventional intra-articular treatment.
The rationale is intriguing: if abnormal biological activity within subchondral bone contributes to joint symptoms, could addressing that environment improve outcomes?
Early clinical findings are mixed. Some studies report improvements in pain and function, while others show no clear additional benefit from intraosseous treatment.
We consider this a promising research direction, but not an established solution. Evidence does not yet demonstrate that these injections reliably resolve BMLs or regenerate cartilage.
It's also important to distinguish osteoarthritis-related lesions from insufficiency fractures, osteonecrosis, and other bone conditions requiring different management.
The RegeneZone Method™: Our Comprehensive Approach
We've organized our approach around four interconnected stages: Evaluate, Optimize, Treat, and Remodel.
Evaluate: Understand the Entire Joint
We begin with a comprehensive examination and diagnostic musculoskeletal ultrasound to assess tendons, ligaments, synovial inflammation, joint fluid, and accessible cartilage surfaces.
When indicated, MRI provides additional information about bone marrow lesions, subchondral bone, cartilage, and meniscal pathology.
We also consider relevant laboratory findings, metabolic health, hormonal status, and other systemic contributors.
Optimize: Improve the Joint Environment
We address modifiable factors that may influence joint health, including excess body weight, insulin resistance, chronic inflammation, nutritional concerns, hormonal deficiencies, and inadequate muscle strength.
Our objective is to improve the patient's overall musculoskeletal health, not simply manage an isolated symptom.
Treat: Individualized Orthobiologic Medicine
Depending on the diagnosis, treatment options may include ultrasound-guided platelet-rich plasma, PRGF, prolotherapy, and other appropriate interventions.
We also follow research involving Wharton's jelly-derived extracellular matrix allografts, mesenchymal stromal cells, and extracellular vesicles.
These emerging fields are advancing our understanding of cellular communication and tissue biology. However, Wharton's jelly-derived products and MSC-derived extracellular vesicles are not FDA-approved treatments for osteoarthritis or cartilage regeneration.
We believe treatment should be individualized, evidence-informed, and appropriate for each patient's condition.
Remodel: Restore Strength and Function
An injection is not the end of treatment.
We emphasize strengthening, biomechanics, appropriate movement, and ongoing assessment.
We want to know whether our patients can walk farther, climb stairs more comfortably, return to activities they enjoy, and maintain their independence.
Those are the outcomes that matter.
The Future of Joint Medicine
For us, bone marrow lesion research represents something larger than a new MRI finding. It reflects a fundamental change in how we understand osteoarthritis.
Cartilage does not exist in isolation. Neither does bone, muscle, synovium, or any other part of the musculoskeletal system.
The entire joint participates in a continuous biological conversation, influenced by the health of the entire person.
This is why we believe the future of joint medicine must combine sophisticated diagnostics with an understanding of inflammation, metabolism, hormones, biomechanics, and orthobiologics.
We cannot promise to reverse every degenerative change or eliminate the need for surgery. But we can evaluate more thoroughly, address modifiable contributors, and develop individualized strategies aimed at improving pain, function, and long-term joint health.
Our goal has never been simply to treat a painful joint. It's to help our patients preserve the strength, mobility, and independence that make a longer life worth living.
Experience The RegeneZone Method™
At RegeneZone™, we combine diagnostic ultrasound, individualized medical evaluation, orthobiologic treatment options, and comprehensive musculoskeletal care.
If you're experiencing chronic joint pain, osteoarthritis, or declining mobility, we invite you to explore a more complete approach.
Schedule your RegeneZone evaluation in Scottsdale or Prescott, Arizona.
Dr. John A. Robinson, NMD & Dr. Cristina Romero-Bosch, NMD
Co-Founders, RegeneZone™
References
Findlay DM, Kuliwaba JS. Bone–cartilage crosstalk: a conversation for understanding osteoarthritis. Bone Research. 2016;4:16028. https://doi.org/10.1038/boneres.2016.28
Roemer FW, et al. Change in MRI-detected subchondral bone marrow lesions is associated with cartilage loss: the MOST Study. A longitudinal multicentre study of knee osteoarthritis. Annals of the Rheumatic Diseases. 2009;68(9):1461–1465. https://doi.org/10.1136/ard.2008.096834
Hunter DJ, et al. Increase in bone marrow lesions associated with cartilage loss: a longitudinal magnetic resonance imaging study of knee osteoarthritis. Arthritis & Rheumatism. 2006. https://doi.org/10.1002/art.21789
Prevalent cartilage damage and cartilage loss over time are associated with incident bone marrow lesions in the tibiofemoral compartments: the MOST study. Arthritis Care & Research. https://pubmed.ncbi.nlm.nih.gov/23178289/
